













Melatonin and Migraine
Melatonin & Migraine

On this pageJump to a section6
Melatonin is a hormone secreted by the pineal gland in the brain that helps coordinate circadian rhythms and the sleep cycles. Light exposure suppresses natural melatonin production while darkness stimulates its release. Melatonin levels typically rise in the evening, remain elevated during sleep, and decline around morning wake-up time.
In addition to sleep regulation, melatonin exhibits anti-inflammatory, antioxidant, and neuromodulator properties. It also influences pain pathways. Both endogenous melatonin production and oral supplementation have proven generally safe across decades of study.
Studies
This study was a randomized, double-blind, placebo-controlled trial evaluating the efficacy and tolerability of melatonin for migraine prevention. 196 patients with 2-8 migraine attacks per month were randomized to receive melatonin 3 mg, amitriptyline 25 mg, or placebo daily for 12 weeks.
Melatonin 3 mg was found to be effective for migraine prevention, with similar efficacy to amitriptyline 25 mg, but better tolerability. Melatonin appeared as effective as other standard migraine preventive medications with a favorable side effect profile.
However, because the randomized controlled trials are still limited, there is still not enough evidence to change clinical practice guidelines and offer melatonin as a treatment.
Melatonin is involved in regulating circadian rhythms and sleep. Melatonin levels and metabolites are LOW in patients with migraine, and sleep disturbances are more common, suggesting a relationship:
https://headachejournal.onlinelibrary.wiley.com/doi/10.1111/head.13828Proposed mechanisms for melatonin benefits in migraine include anti-inflammatory effects, increasing β-endorphin, membrane stabilization, stimulating GABA receptors, and inhibiting neuropeptide release. Animal studies also show effects on cortical spreading depression pathways by decreasing trigeminal nociceptive activation.
Pathogenic Role of Melatonin in Migraine
Melatonin exerts effects through melatonin receptors (MT1 and MT2) located throughout the central nervous system and peripheral tissues.
https://www.ncbi.nlm.nih.gov/pmc/articles/PMC9415653/Disturbances in normal melatonin patterns are likely to contribute to migraine attacks. Several studies have shown migraine patients have significantly decreased melatonin levels during acute migraine attacks as well as blunted nighttime melatonin secretion.
It is hypothesized that this results from dysfunction in the hypothalamic-pineal axis, which normally controls melatonin synthesis.
Specifically, the suprachiasmatic nucleus (SCN) in the hypothalamus dictates melatonin production in response to light exposure mediated through a retinal-hypothalamic pathway. In migraine patients, abnormalities along this pathway lead to impaired SCN communication and inhibition of melatonin release from the pineal gland. Hypothalamic dysfunction is thought to play a role in triggering migraine based on its connections with trigeminal pain centers.
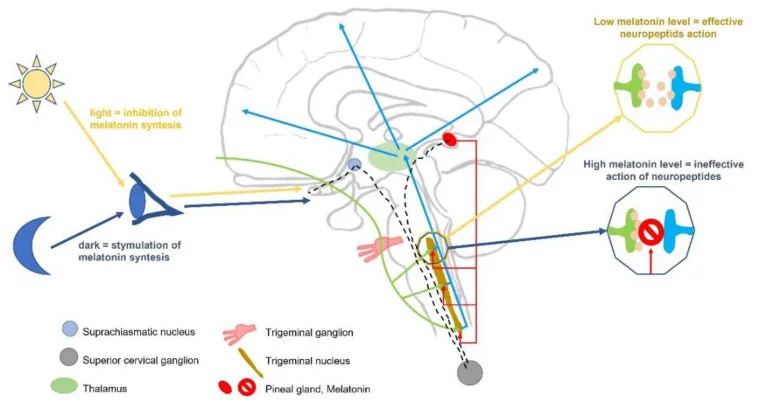
Restoring normal melatonin levels may break this pathological process. Melatonin has antioxidant, anti-inflammatory, and neuromodulator properties that inhibit several mechanisms in migraine development.
This includes dampening trigeminal nerve excitation, neurogenic inflammation, and release of calcitonin gene-related peptide (CGRP), and substance P - vasodilatory neuropeptides central to migraine pain signaling.
https://link.springer.com/article/10.1007/s11055-017-0472-5Furthermore, melatonin enhances GABAergic transmission, thereby raising the brain's pain activation threshold typically disturbed in patients with migraine. It also modulates dopamine, serotonin and intracellular calcium signaling implicated in migraine as well.
https://pubmed.ncbi.nlm.nih.gov/16548786/Through these myriad effects, melatonin supplementation shows promise as a prophylactic therapy for migraine prevention and management.
https://pubmed.ncbi.nlm.nih.gov/30653130/Melatonin, Migraine, and Sleep
Research shows melatonin levels are low in groups prone to migraine. Additionally, sleep disturbances strongly impact migraine patterns. Insufficient or irregular sleep commonly triggers attacks while quality sleep can relieve them. Unfortunately, recurring pain makes restorative sleep elusive for many people with migraine.
This two-way relationship between migraine activity and sleep highlights the potential for therapies that target sleep-wake cycles and melatonin regulation. Correcting melatonin deficits could theoretically restore normal circadian physiology, improve sleep quality, reduce migraine frequency and pain levels.
Dosage
Positive outcomes correlate with higher melatonin doses in some analyses. 3-5 mg nightly for 2-3 months is suggested.
Safety
Animal and human studies show that short-term and long-term use of melatonin is safe, even at very high doses. And the adverse effects are comparable to placebo.
Source: https://pubmed.ncbi.nlm.nih.gov/26692007/
This study found long-term melatonin use safe and effective for kids with ADHD sleep problems:
https://onlinelibrary.wiley.com/doi/abs/10.1111/j.1600-079X.2009.00681.xResearchers followed up with 94 school-aged kids with ADHD who had chronic sleep onset insomnia (trouble falling asleep) and had previously participated in a melatonin study. After almost 4 years, over half were still taking melatonin every night at bedtime.
The good news- melatonin was still effective, with 88% of parents rating it as effective against sleep problems. Even better, 71% said their child's behavior improved, and 61% noticed a positive difference in their child's mood.
On the safety front, there were no serious side effects or medical issues caused by long-term use.
Additional Resources
For more information on melatonin and migraine, see this well-written article by Migraine Again:
https://www.migraineagain.com/melatonin-and-migraine-sleep-hormone-headache/


Cerebral Torque
Founder of Cerebral Torque and author of Unraveling Migraine, with a medical background. Trained in computational and cellular neuroscience, with research using Hodgkin-Huxley modeling and clamp electrophysiology to study how neurons respond to rhythmic input. Now focused on migraine medicine and education, and has produced CME for clinicians on hormone therapy, migraine, and HRT delivery.
More about the authorThis article is for education and is not medical advice. Talk with your own clinician before starting, stopping or changing any treatment.
Non-drug and natural options

Complete Guide to Neuromodulation Devices for Migraine Treatment
A comparison of FDA-cleared migraine devices, with protocols, evidence and side effects.
HeadaTerm 2: An Affordable FDA-Cleared Alternative to Cefaly for Migraine Relief
HeadaTerm 2 is an FDA-cleared device similar to Cefaly at a fraction of the price.

Can a Wearable Predict a Migraine Attack? What a New Wrist-Sensor Study Found
A new Cephalalgia study paired a wrist-worn sensor with personalized machine learning and flagged pre-attack periods 2 to 12 hours before the headache started in most…